Planning your umbilical hernia surgery and recovery
If recovery worries you, the first days are usually managed with simple pain relief
Dr Daniel Lee, FRCS (Edinburgh), is a former Head of Colorectal Surgery at Khoo Teck Puat Hospital.

What an umbilical hernia is, and why the belly button is a natural weak point
An umbilical hernia is a bulge at or near the belly button.
A hernia happens when part of the bowel or other soft tissue pushes through a weak spot in the muscle wall. The belly button sits over a natural weak point in the abdominal wall, where the umbilical cord once passed through.
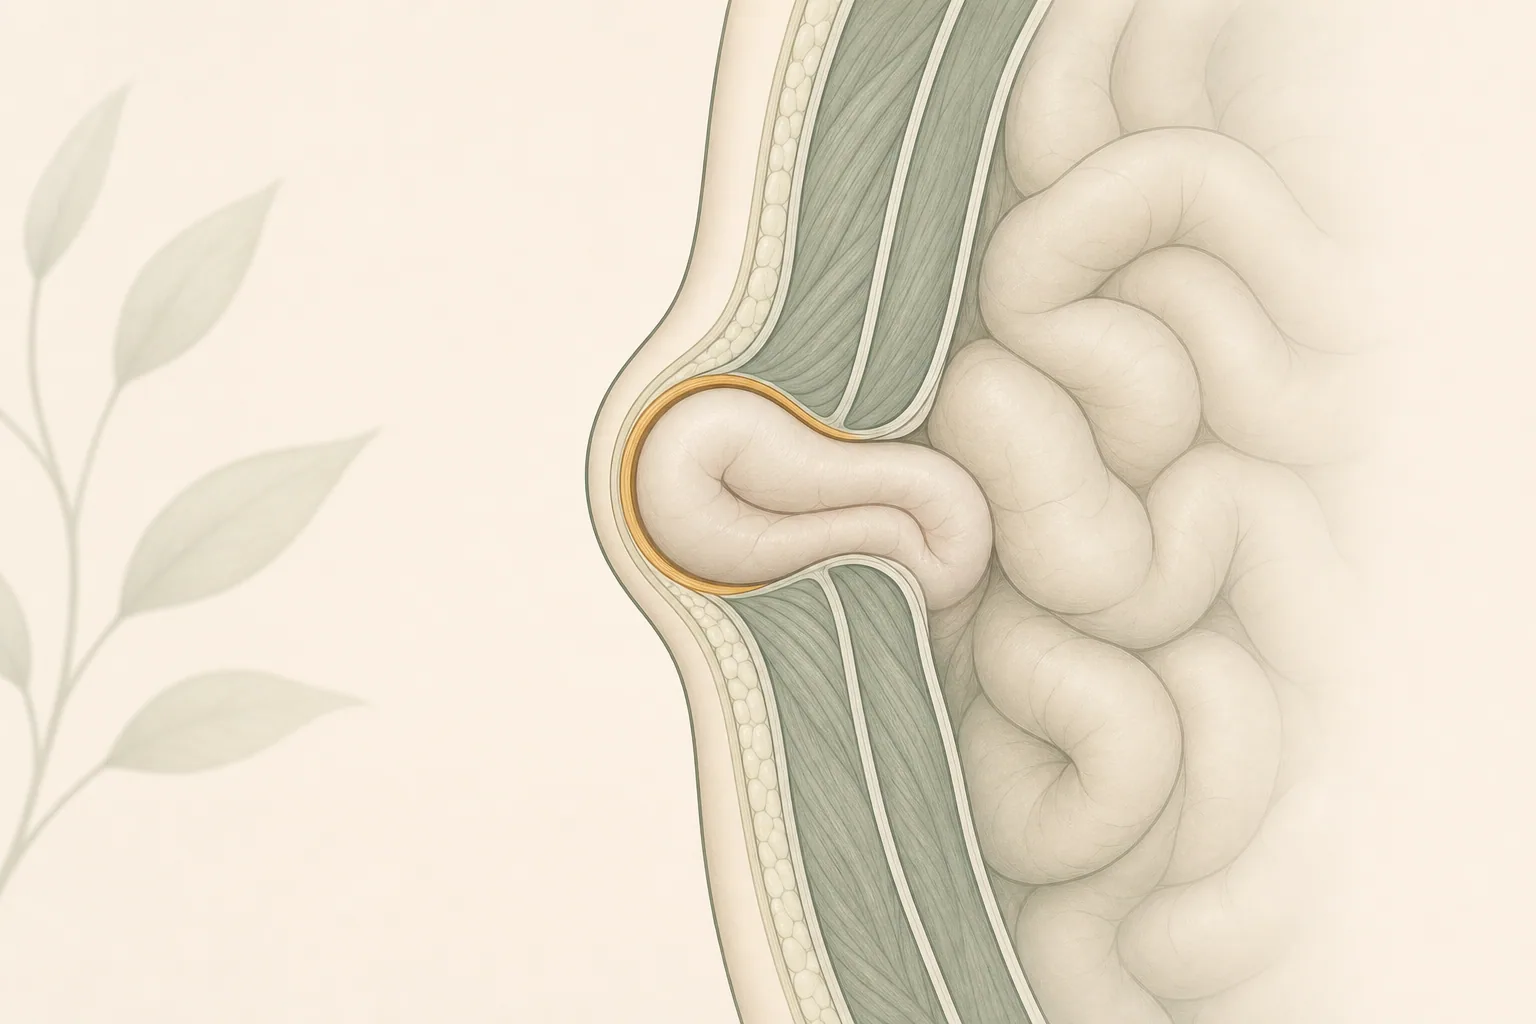
The bulge comes and goes. It is often more obvious when you stand, cough, laugh or strain, and it flattens when you lie down. In adults it is common after pregnancy or with weight gain.
A hernia often barely hurts at first, which is why many people wait for months or even years.
A hernia that sits just above or below the navel rather than through its centre is called a paraumbilical hernia. It is assessed and repaired on the same principles.
This page is for adults: Dr Lee does not treat children's hernias, and a child with a bulge at the navel should see a children's surgeon. The main hernia surgery page covers how each repair works, recovery and insurance.
Umbilical hernia symptoms to look for, and the signs that cannot wait
A bulge at the navel deserves a proper examination even when it does not hurt, because the plan depends on what the hernia is doing. These signs mean the hernia should be seen soon.
- You can see or feel a soft bulge at or beside the belly button, with or without discomfort.
- You notice an ache, a dragging feeling or pressure at the navel after standing or exertion.
- The bulge is getting larger or more uncomfortable over time.
- The skin over the bulge looks thin, stretched or irritated.
- A bulge that used to push back in no longer does.
- You are planning a pregnancy or an operation and want the hernia assessed first.
A navel bulge that turns very painful and firm needs urgent care
Rarely, a hernia can become trapped and lose its blood supply, which is called strangulation. A very painful, firm bulge that will not push back in, or one that comes with nausea, vomiting or red or discoloured skin, is a warning sign. If your hernia suddenly becomes very painful and firm or will not push back in, do not wait. Go straight to the nearest A&E or contact us immediately.

Pregnancy, weight gain and the tummy gap, and how rectus diastasis differs from a hernia
Pregnancy and weight gain are two of the situations in which an umbilical hernia is common in adults, and a bulge is often first noticed during or after a pregnancy.
If you may have another pregnancy, tell Dr Lee before any repair is planned: a 2020 guideline on ventral hernias in special circumstances advises postponing repair until after the last pregnancy, where possible, because a later pregnancy raises the chance of the hernia coming back.
A tummy gap, also called rectus diastasis, is a widening between the muscles rather than a weak spot in the wall, and the European Hernia Society guideline on rectus diastasis defines it as a separation between the rectus muscles wider than 2 cm.
For a tummy gap on its own, the same guideline says physiotherapy may be considered before surgery, and when a midline hernia comes with the gap, it suggests a mesh-based repair.
Dr Lee examines you to tell which one you have, or whether you have both, and explains the approach planned for your own case.
Watching a small hernia that barely hurts, and when repair becomes the next step
Dr Lee says a hernia operation rarely needs to be rushed, but a hernia does not repair itself and will slowly get bigger. The bowel can also get trapped in the gap, and that can mean an emergency operation.
A small, soft hernia that causes no symptoms can sometimes be watched, and Dr Lee says plainly when that is a reasonable path. The 2020 guideline recommends that a hernia with symptoms be repaired.
A planned repair is often done as day surgery, while the same hernia repaired as an emergency usually needs a hospital stay, and the bill is higher.

Stitches or mesh, open or keyhole, and how the repair is done
Umbilical hernia surgery repairs the weak spot in the muscle wall, and Dr Lee describes most hernia repairs the same way: the bowel is first eased back into place, and then a small piece of surgical mesh strengthens the weak spot.
The 2020 European and Americas Hernia Societies guideline for umbilical and epigastric hernias recommends mesh to reduce the chance of the hernia coming back. It also says the evidence is limited, so most of its recommendations are graded as weak.
Open repair, the usual route in the guideline
The guideline says most umbilical hernias may be repaired by an open approach, with a flat mesh placed behind the muscle wall. Open repair is done through a small cut at the navel.
When keyhole repair may be considered
The guideline says a laparoscopic, or keyhole, approach may be considered if the gap is large or if wound problems are more likely. Keyhole repair, which Dr Lee describes as either laparoscopic or robotic assisted, uses a few small cuts instead of one long one.
Repair with mesh and repair without mesh
Mesh is the guideline's main recommendation, and Dr Lee explains the approach planned for you, including when a repair without mesh is more appropriate. Whether stitches alone are enough is a decision made for your hernia, after he has examined it.
A repair matched to your hernia and your health
Dr Lee is a hernia and colorectal surgeon who performs both open and keyhole repair. He recommends one way of repairing the hernia based on your hernia, your health and your history, and explains why before anything is decided.
What the Ministry of Health fee benchmarks show for an umbilical or epigastric hernia repair
The Ministry of Health publishes fee benchmarks for the surgeon and the anaesthetist. The one below is for an umbilical or epigastric hernia repair and includes GST.
Hernia assessment with Dr Lee: SGD 150
| Type of repair | MOH surgeon fee benchmark (with GST) | MOH anaesthetist fee benchmark (with GST) |
|---|---|---|
| Belly-button or upper-abdomen herniaumbilical or epigastric, SF814A | SGD 3,270 to 5,341 | SGD 1,199 to 1,962 |
These are national benchmarks before MediSave and insurance, not Dr Lee's own fee, and the hospital fee is charged separately.

Most hernia repairs are done as day surgery, with simple pain relief for the first days
Your own plan for umbilical hernia surgery is confirmed at your consultation, once Dr Lee has examined the hernia.
These are typical times after most hernia repairs, not a promise, and your own recovery depends on the repair, your health and your work.
Home the same day
Dr Lee describes most hernia repairs as day surgery, and the first few days are usually managed with simple pain relief.
Back to light duty
For most hernia repairs, most patients are back to light duty in one or two weeks, and desk work is usually earlier.
Usual activities
By around three months most people are back to all their usual activities, including heavy lifting.
Questions about umbilical hernia repair, answered plainly by Dr Daniel Lee
What are the first days like after the operation, and how is the pain managed?
Dr Lee describes most hernia repairs as day surgery, which means you go home the same day. The first few days are usually managed with simple pain relief, and walking and light daily tasks can start straight away.
For most hernia repairs, Dr Lee says most patients are back to light duty in one or two weeks, and desk work is usually earlier. These are typical times, not a promise, and Dr Lee goes through what to expect in your own case.
When can I drive, exercise and lift again after the repair?
Dr Lee's hernia surgery page says most people are back at a desk job and driving within one to two weeks. It advises driving only once you can make an emergency stop without pain and are no longer taking medicine that makes you drowsy.
Over the following weeks you can build back up to gym work, running and sport, starting light and letting comfort set the pace. By around three months most people are back to all their usual activities, including heavy lifting, and pain that is still there at three months should be checked rather than put up with.
These are the general times for a planned hernia repair, and Dr Lee confirms what applies to you.
Is an umbilical hernia operation major or minor, and should I be worried?
The 2020 European and Americas guideline describes umbilical and epigastric hernia repairs as frequently performed operations with an expected low complication rate.
Most hernia repairs are day surgery, so you go home the same day. Before the operation your fitness for anaesthesia is assessed, including any heart, lung or diabetes considerations, and Dr Lee explains each step before anything is decided.
It is a fair thing to feel nervous about before a first operation, and Dr Lee explains the approach planned for you and why.
Is the hernia repaired with stitches or mesh, and by open or keyhole surgery?
Mesh is the main recommendation of the 2020 guideline, to lower the chance of the hernia coming back, and most umbilical hernias may be repaired by an open approach with a flat mesh placed behind the muscle wall.
A keyhole approach may be considered if the gap is large or if wound problems are more likely. Keyhole repair uses a few small cuts instead of one long one.
Dr Lee performs both open and keyhole repair and explains the approach planned for you, including when a repair without mesh is more appropriate.
Can I leave an umbilical hernia alone, or will it need repair in the end?
A hernia does not repair itself and will slowly get bigger, and the bowel can get trapped in the gap, which can mean an emergency operation. Dr Lee says a hernia operation rarely needs to be rushed.
The guideline recommends that a hernia with symptoms be repaired. A small, soft hernia that causes no symptoms can sometimes be watched, and Dr Lee says plainly when that is a reasonable path.
A bulge that becomes very painful and firm, or will not push back in, should not wait.
How do I know a bulge at the belly button is an umbilical hernia?
An umbilical hernia usually shows as a bulge at or near the navel that comes and goes. It is often more obvious when you stand, cough, laugh or strain, and it flattens when you lie down.
Many people feel a dragging ache at the navel by the end of the day.
Dr Lee examines you standing and lying down, which shows what is coming through and how readily it pushes back in. A tummy gap, called rectus diastasis, is a separate condition that can sit beside a hernia, and he explains which one applies to you.
How much does umbilical hernia repair cost?
The Ministry of Health benchmark for the surgeon's fee for an umbilical or epigastric hernia repair is SGD 3,270 to 5,341 with GST, and for the anaesthetist SGD 1,199 to 1,962. These are national benchmarks, not Dr Lee's fees, and the hospital fee is charged separately.
MediSave can be used for eligible hernia surgery within MOH limits, and Integrated Shield plans usually cover it, depending on your policy. The team gives you a written estimate before anything is booked.
Five private hospitals, one team.
Other types of hernia, and the main hernia surgery page
A short message to the clinic is enough to start the conversation
Send a note with your name, number and what you are noticing, whether the bulge appeared last week or you have lived with it for years. Dr Lee's team will reply on WhatsApp and arrange a time and location that suits you.